

Quote of the Day
“It has become appallingly obvious that our technology has exceeded our humanity.”
Albert Einstein – Physicist (1879 – 1955)
The “98.2% Long COVID Reduction” That Is Almost Certainly Missing the Disease Itself
A massive new study suggests that far fewer long-term conditions can be attributed to COVID-19 when researchers compare PCR-positive and PCR-negative patients. They are dismissing so much.
Walter M Chesnut
Sometimes something is published (more often so, these days) that is so seriously wrong that it must be addressed. No matter how ridiculous it is. A newly published study in the Proceedings of the National Academy of Sciences has generated considerable attention by reporting a 98.2% reduction in the number of clinical outcomes statistically attributable to COVID-19 when researchers changed how they selected their control population. This is one such seriously wrong, ridiculous example.
The study, Revised estimates of types and duration of long COVID symptoms based on claims records from 245 million US patients, analyzed an extraordinary 14.4 billion insurance claims from approximately 245 million Americans. The investigators compared patients who tested positive for SARS-CoV-2 with patients who tested negative, rather than relying on broader populations that included people who had never been tested.
The results were dramatic.
Between 120 and 359 days after testing, the number of clinical outcomes statistically attributed to COVID-19 declined from 286 to just five.
A 98.2% reduction.
There is a crucial distinction we must acknowledge here: this was not a 98.2% reduction in the number of people suffering from Long COVID. It was a reduction in the number of outcome categories that met the researchers’ criteria for attribution to COVID-19.
The “authors” of the study are IGNORING (intentionally, they can’t be this stupid) some extraordinarily important FACTS.
Some of the people who tested negative had almost certainly already developed Long COVID from an earlier infection that was never documented. Some of the people who tested negative almost certainly had been given Spike mRNA/injections.
A Negative PCR Test Is Not a Negative Infection/Exposure History
The central premise of the researchers’ approach is absurd. People who undergo COVID testing may differ from people who never seek testing. They may have underlying medical conditions, more frequent healthcare encounters, or other reasons for receiving medical attention. They also may prefer apples to oranges…
All a negative PCR test establishes is that SARS-CoV-2 was not detected in that particular sample at that particular time. It does not establish that the individual had never been infected. Or that they had never been exposed to the Spike Protein via mRNA/vaccination.
Most importantly, it certainly does not establish that an earlier infection/exposure had not initiated a chronic pathological process. Indeed, the National Academies’ 2024 definition of Long COVID explicitly recognizes that the condition can follow an infection that was never clinically recognized or laboratory-confirmed. The CDC likewise states that a positive SARS-CoV-2 test is not required for a Long COVID diagnosis.
A person can have Long COVID without ever having had a documented positive SARS-CoV-2 test.
This is not a controversial proposition. It is part of the accepted clinical understanding of the condition.
From the CDC itself:
Long COVID is not one illness. There is no approved laboratory test that can determine if your symptoms or conditions are due to Long COVID. A positive SARS-CoV-2 test is not required for a Long COVID diagnosis.
Long COVID Basics
https://www.cdc.gov/long-covid/about/index.html
What If the Macrophage Was Already Smoldering?
This is where my Smoldering Macrophage Syndrome (SMS) hypothesis becomes relevant.
I have proposed that SARS-CoV-2 infection/Spike exposure may initiate persistent, tissue-localized macrophage activation that continues long after the acute infection has resolved or Spike exposure occurred. In this model, the initiating infection/exposure and subsequent disease process are not necessarily simultaneous.
The virus may no longer be detectable in the upper respiratory tract. Circulating inflammatory markers may be unremarkable. Yet macrophages residing in tissues such as the lungs, heart, brain, gut, and microvasculature could remain abnormally activated, contributing to persistent inflammatory signaling, endothelial dysfunction, and tissue remodeling.
This remains a hypothesis requiring direct validation. But consider what it would mean for the interpretation of this enormous epidemiological study. Imagine an individual who experienced an undocumented SARS-CoV-2 infection months earlier, or Spike Protein exposure.
That individual could now enter the study’s comparison population despite already having a post-COVID/Spike Exposure condition.
If this occurred frequently enough, the supposedly uninfected comparison group could contain people with the very disease processes the researchers were attempting to attribute to COVID-19.
I am absolutely stunned that this nonsense was published. (Or am I?) And yes, it’s dangerous. It not only is inaccurate about the potential prevalence of Long COVID, it also indirectly seeks to dismiss the suffering of millions who are dealing with this horrific disease state. The “study” should be immediately retracted and with formal apologies from the publisher. We will not tolerate such manipulation of data or dismissal of the anguish of millions of individuals.
A Good Man Without Strength

We Are Still In An Ice Age

Earth is still in an ice age right now — we are just in a warm pause and the glaciers will advance again
Click to view the video: https://www.facebook.com/share/p/1EhQQRt3Ro/
Quote of the Day
“There has never been a good war or a bad peace.”
Benjamin Franklin – Founding Father, statesman, diplomat (1706 – 1790)
The System Protects The System










The system acts to protect the system, not the public. Your increasing knowledge, expanding awareness and continued vigilance are your best defences against a system designed and managed to protect itself, not you.
Best Protein For Muscle Mass

Pfizer COVID Vaccine Deadly
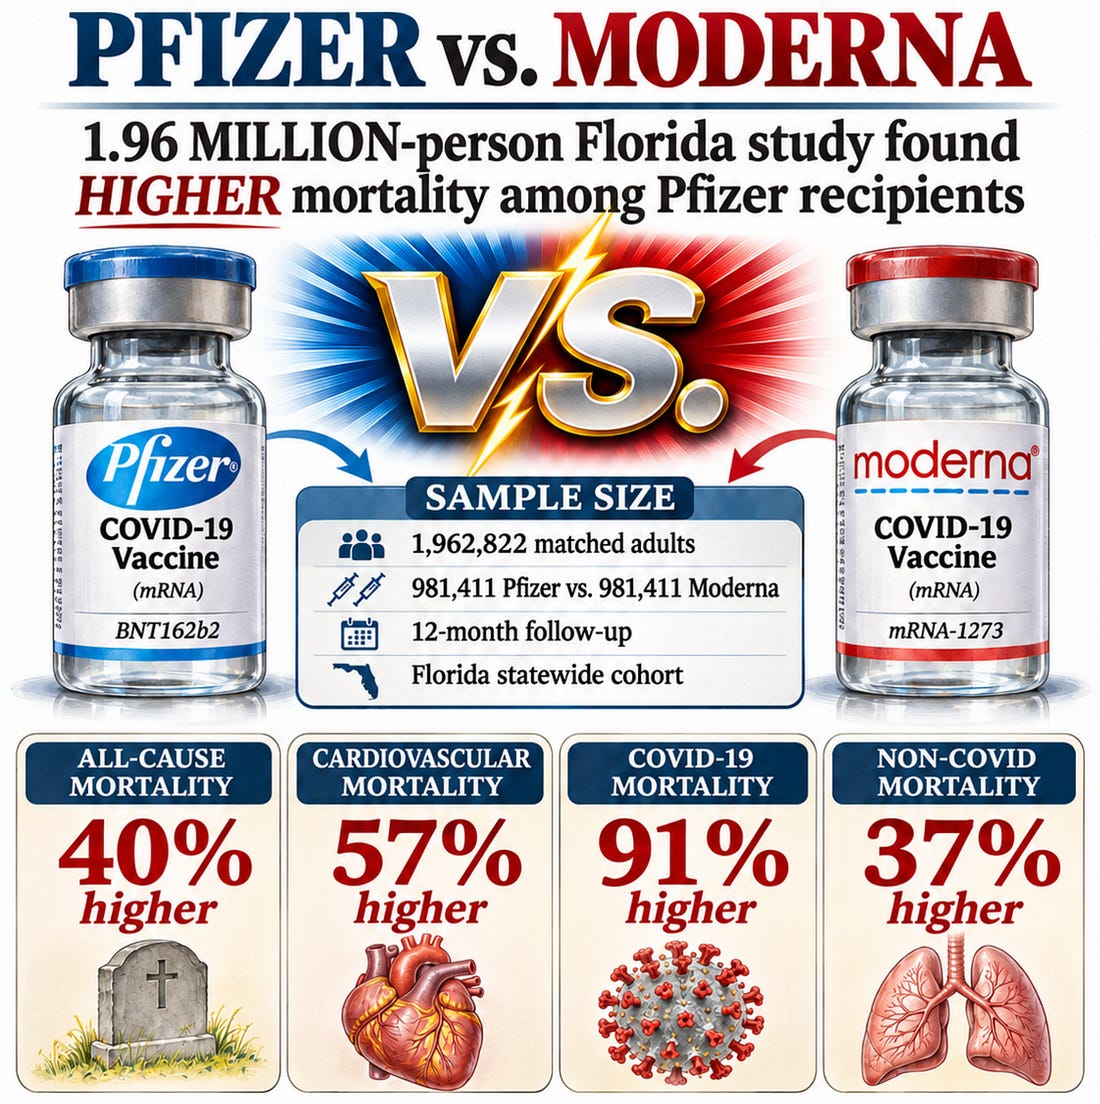
Pfizer doesn’t want you to know this. This information doesn’t appear in any of their ads for the COVID vaccine for some reason. Baffling for sure!
Executive summary
The easiest way to tell if you are talking to someone who is intellectually honest about the COVID vaccines is to ask them for their assessment of the Levi paper.
If they claim, like UPenn Professor Jeffrey Morris does, that there is nothing to see here, then you are dealing with someone who is intellectual dishonest. The AI analysis of Morris’s attack on the Levi paper is absolutely devastating.
What the paper found
37% higher non-COVID mortality in people who got Pfizer.
That’s a train wreck.
There is no other way to spin this.
Possible explanations for the results:
The Pfizer/Moderna groups weren’t really matched
Moderna reduces non-COVID all-cause mortality by 37%
The problems:
They were matched. Barbra Dickerman wrote 2 papers on COVID vaccines and VA data showing that crude demographic matching creates extremely good morbidity matching to nobody’s surprise. But Levi’s matching was MUCH stronger than what Dickerman did (more attributes and tighter matches). And he confirmed the matching by looking at the single most devastating statistic: prior cardiovascular hospitalization rates were matched. This is not a random marker — it’s arguably the single most mortality-relevant clinical signal you can extract from administrative data. So we have no reason to believe the groups weren’t matched and every reason to believe they were.
There is no mechanism of action that could possibly explain how a COVID vaccine can reduce non-COVID all-cause mortality by 37%. If that were true, this would be the most amazing drug ever created. Moderna would be marketing their COVID vaccine as a fountain of youth. Everyone would be taking it. We’d have seen dramatic reduction in all cause mortality all over the world after rolling out the drug. No such data exists. If you plot cumulative COVID deaths over time for the world, the rollout of the vaccine didn’t change the slope one bit which means the COVID shots didn’t really save any lives. But people who opt to taking vaccines have lower mortality in general, but it is NOT caused by vaccines; it is 100% selection bias. People who opt for vaccines tend to have better access to healthcare.
The full discussion is here and it’s worth reading.
The bottom line
No two ways about it. The COVID vaccines were deadly.
They should be taken off the market.
It is absolutely appalling that businesses and schools forced people to take a vaccine that can increase mortality by 37%. But nobody is willing to talk about it, and no business has formally apologized for their mistake.
Those who want to talk about, like Professor Morris, cherry pick the evidence to support their point of view. These people are extremely dangerous. The AI analysis of Morris’s attack on the Levi paper is absolutely devastating.
Where is the outrage?
Every member of Congress should be shocked by this paper. They should be calling for replication of this study in all 50 states.
Don’t they want to know that they were responsible for over 500,000 American deaths?
Can you name one member of Congress doing that? With 535 members, you’d think that there would be at least one honest member speaking out asking for similar studies to be done, wouldn’t you?
Not one.
They don’t want to know.
Summary
The Levi paper is clear: 37% higher mortality if you got Pfizer.
None of the “explanations” can explain this difference.
Nobody is calling for more studies to replicate the Levi study.
And the Levi study was rejected by around 12 journals before being published showing you just how corrupt “science” is.
https://open.substack.com/pub/stevekirsch/p/levi-paper-showing-pfizer-is-a-toxic
You Can Still Change
