Measles Vaccine Is Gain-of-Function Product, Even On Mainstream Disease Model: CD150/CD46 Tropism

No studies confirm the measles vaccine virus is less infectious or replicates less in humans than the wild-type measles virus.
Jon Fleetwood

Sources: The Journal of Infectious Diseases (2015) and Congressional Research Service (CRS). The peer-reviewed journal identifies the development of the live-attenuated measles vaccine through repeated passage and altered viral tropism as potentially qualifying as gain-of-function research, while Congress’s research service defines GOF as genetic mutations that confer “a new or enhanced ability.”

On the mainstream virological model, a May 2016 publication in The Journal of Infectious Diseases by U.S. military biodefense experts states that the live-attenuated measles vaccine was created by a process that “could be considered, by current definitions, GOF research.”

The paper states: “The live-attenuated measles vaccine was created by passaging the virus until mutations arose that altered virus tropism—a technique that could be considered, by current definitions, GOF research.”

Keep reading: https://jonfleetwood.substack.com/p/measles-vaccine-is-gain-of-function

Why COVID Vaccine Injuries Persist and What Patients Report Has Helped

Built To Linger

Story at-a-glance

The COVID vaccines were sold as a transient exposure: a short burst of spike protein that the body would clear within days. Published studies have since found vaccine mRNA and spike protein in the body for months, and in some cases for more than two years.

This persistence may help explain why so many injuries never resolved, why many people react to each subsequent vaccine or COVID infection, and why a subset of the unvaccinated became ill around the recently vaccinated.

The safety monitoring data the CDC collected (and fought to keep from the public) showed that 7.7% of the 10 million participants needed medical care after vaccination, and an independent audit of Pfizer’s trial, using data released by court order, documented 1,203 participants vanishing from the records.

Treating these injuries has been left to a handful of practitioners working independently, and comparing notes with the ones getting the best results shows that many therapies appear to fail not because they don’t work, but because they are given at the wrong point.

The interventions patients rate most helpful are the affordable ones rarely promoted, and many patients improve once they stop taking most of what they have been sold.

More Excerpts
Beyond the mRNA platform still being experimental when it was given to the entire population, a lot of very strange things happened after the rollout, which invited equally strange explanations, and I spent years sorting out which of those observations were real.

Three held up. The spike protein does not leave the body the way it was supposed to, a subset of people around the vaccinated became ill in consistent patterns, and the resulting injuries are now one of the most widespread and complex illnesses the population faces, with almost no mainstream research on them and no established way to treat them. Since I am continually asked what can actually be done, this article is the result of a large project by numerous clinicians to answer that question.

Note: One of the stranger observations of this period was embalmers reporting large rubbery clots in the bodies of the vaccinated, which citizen researchers documented through surveys that were eventually published in a medical journal.25 In 2021, a laboratory study found that adding spike protein to the plasma of healthy volunteers caused fibrin (the protein the body builds clots from) to misfold into dense amyloid clots that resisted being broken down.26

Since the body continually forms and dissolves fibrin clots, I reasoned that clots the body could not dissolve would keep growing until they took the shape of the vessels containing them, which has since been put forward by others as an explanation for what the embalmers were finding.

Shedding
Once the vaccines came out, I began to hear numerous similar reports of people who had made a point not to vaccinate becoming ill after being around someone who had, particularly if they had recently been vaccinated or the contact was prolonged. Menstrual abnormalities were the most common, to the point that several of my post-menopausal friends began experiencing immediate and significant bleeding.

Since the vaccines “by definition” could not shed, this was dismissed each time it was raised, so with Pierre Kory’s help I collected provider data on it, put out a call for readers to share their experiences, and searched the literature for everything known about shedding.

From the more than 2,000 reports I compiled, the most frequently reported symptoms (in rough order of frequency) were abnormal menstrual bleeding (which far outnumbered everything else), headaches, rashes, flu-like illnesses, tinnitus, fatigue, dizziness, nosebleeds, unexplained bruising, shingles, a distinct odor around the vaccinated, palpitations, coughs, sinus congestion, muscle pain, gastrointestinal issues and brain fog.

Relatedly, a 2023 peer-reviewed study found spike protein antibodies in the noses of unvaccinated children of vaccinated parents, and on the surgical masks worn by vaccinated adults, leading the authors to hypothesize that antibody transfer was occurring through the breath. Likewise, two studies detected vaccine mRNA within the breast milk exosomes of recently vaccinated mothers.

Note: Since spike protein toxicity appears to be cumulative, most vaccine injured patients quickly realize each subsequent vaccine makes them worse, in some cases COVID infections do too, and in the most sensitive, shedding exposures worsen their condition, making appropriate spike avoidance an important component of recovery…

…Conclusion
A novel protein was introduced into essentially every human being on earth and is demonstrably capable of causing disease in a subset of them, so “spikeopathy” should by now be a recognized discipline with its own researchers, diagnostics, and literature. Instead, as Kory put it to me, there are a handful of practitioners figuring it out independently while conventional medicine maintains the illness does not exist….

…On the dietary side, no single diet outshone the rest (the most used were low histamine, intermittent fasting, gluten free and paleo type diets, along with eliminating seed oils and eating organic), so what appears to matter is simply getting off the standard American diet…

Finish reading: https://articles.mercola.com/sites/articles/archive/2026/11/13/covid-vaccine-injuries-spike-protein.aspx

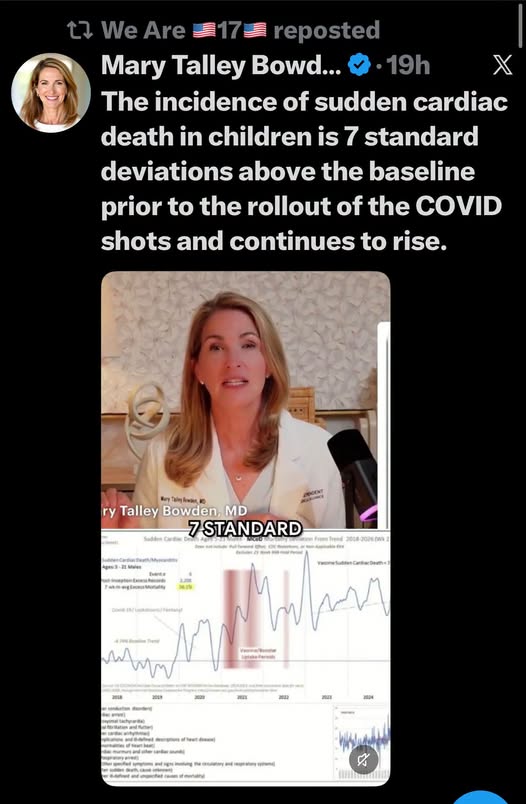
Seven Standard Deviations

Seven Standard Deviations

For those of us who did not study statistics, ‘standard deviation’ measures how spread out data is from the average. So seven standard deviations is huge!

The “98.2% Long COVID Reduction” That Is Almost Certainly Missing the Disease Itself

A massive new study suggests that far fewer long-term conditions can be attributed to COVID-19 when researchers compare PCR-positive and PCR-negative patients. They are dismissing so much.
Walter M Chesnut

Sometimes something is published (more often so, these days) that is so seriously wrong that it must be addressed. No matter how ridiculous it is. A newly published study in the Proceedings of the National Academy of Sciences has generated considerable attention by reporting a 98.2% reduction in the number of clinical outcomes statistically attributable to COVID-19 when researchers changed how they selected their control population. This is one such seriously wrong, ridiculous example.

The study, Revised estimates of types and duration of long COVID symptoms based on claims records from 245 million US patients, analyzed an extraordinary 14.4 billion insurance claims from approximately 245 million Americans. The investigators compared patients who tested positive for SARS-CoV-2 with patients who tested negative, rather than relying on broader populations that included people who had never been tested.

The results were dramatic.

Between 120 and 359 days after testing, the number of clinical outcomes statistically attributed to COVID-19 declined from 286 to just five.

A 98.2% reduction.

There is a crucial distinction we must acknowledge here: this was not a 98.2% reduction in the number of people suffering from Long COVID. It was a reduction in the number of outcome categories that met the researchers’ criteria for attribution to COVID-19.

The “authors” of the study are IGNORING (intentionally, they can’t be this stupid) some extraordinarily important FACTS.

Some of the people who tested negative had almost certainly already developed Long COVID from an earlier infection that was never documented. Some of the people who tested negative almost certainly had been given Spike mRNA/injections.

A Negative PCR Test Is Not a Negative Infection/Exposure History

The central premise of the researchers’ approach is absurd. People who undergo COVID testing may differ from people who never seek testing. They may have underlying medical conditions, more frequent healthcare encounters, or other reasons for receiving medical attention. They also may prefer apples to oranges…

All a negative PCR test establishes is that SARS-CoV-2 was not detected in that particular sample at that particular time. It does not establish that the individual had never been infected. Or that they had never been exposed to the Spike Protein via mRNA/vaccination.

Most importantly, it certainly does not establish that an earlier infection/exposure had not initiated a chronic pathological process. Indeed, the National Academies’ 2024 definition of Long COVID explicitly recognizes that the condition can follow an infection that was never clinically recognized or laboratory-confirmed. The CDC likewise states that a positive SARS-CoV-2 test is not required for a Long COVID diagnosis.

A person can have Long COVID without ever having had a documented positive SARS-CoV-2 test.

This is not a controversial proposition. It is part of the accepted clinical understanding of the condition.

From the CDC itself:

Long COVID is not one illness. There is no approved laboratory test that can determine if your symptoms or conditions are due to Long COVID. A positive SARS-CoV-2 test is not required for a Long COVID diagnosis.

Long COVID Basics
https://www.cdc.gov/long-covid/about/index.html

What If the Macrophage Was Already Smoldering?

This is where my Smoldering Macrophage Syndrome (SMS) hypothesis becomes relevant.

I have proposed that SARS-CoV-2 infection/Spike exposure may initiate persistent, tissue-localized macrophage activation that continues long after the acute infection has resolved or Spike exposure occurred. In this model, the initiating infection/exposure and subsequent disease process are not necessarily simultaneous.

The virus may no longer be detectable in the upper respiratory tract. Circulating inflammatory markers may be unremarkable. Yet macrophages residing in tissues such as the lungs, heart, brain, gut, and microvasculature could remain abnormally activated, contributing to persistent inflammatory signaling, endothelial dysfunction, and tissue remodeling.

This remains a hypothesis requiring direct validation. But consider what it would mean for the interpretation of this enormous epidemiological study. Imagine an individual who experienced an undocumented SARS-CoV-2 infection months earlier, or Spike Protein exposure.

That individual could now enter the study’s comparison population despite already having a post-COVID/Spike Exposure condition.

If this occurred frequently enough, the supposedly uninfected comparison group could contain people with the very disease processes the researchers were attempting to attribute to COVID-19.

I am absolutely stunned that this nonsense was published. (Or am I?) And yes, it’s dangerous. It not only is inaccurate about the potential prevalence of Long COVID, it also indirectly seeks to dismiss the suffering of millions who are dealing with this horrific disease state. The “study” should be immediately retracted and with formal apologies from the publisher. We will not tolerate such manipulation of data or dismissal of the anguish of millions of individuals.

The System Protects The System

The System Protects The System The System Protects The System The System Protects The System The System Protects The System The System Protects The System The System Protects The System The System Protects The System The System Protects The System The System Protects The System The System Protects The System


The system acts to protect the system and those in charge, not the public.

Increasing your own knowledge, competence and productivity, expanding your awareness and your continued vigilance are your best first line of personal defence against a system designed and managed to protect itself, not you.

“The highest activity a human being can attain is learning for understanding, because to understand is to be free.” – Spinoza, Dutch Philosopher (1632 – 1677)

Helping others to also increase their awareness, knowledge, competence and production is the next level in replacing the present system with a more equitable one.

Vaclav Havel was a Soviet dissident who wrote the book, “Power of the Powerless”. He went on to become the president of the Czech Republic.

He said, “The most powerful weapon against the state is parallel construction. More powerful that combat, protest, or anything else.”

I have seen similar written elsewhere by Buckminster Fuller:
“You never change things by fighting the existing reality.

To change something, build a new model that makes the existing model obsolete.”

So step three is to get busy building a new model that makes the existing system obsolete.

For many years I have had a saying, “It is hard for a person to rise to a higher level of awareness when their attention is being dragged down to a sick or malnourished body.”

If you would like some assistance on step 1 or 2 or 3, please feel free to reach out to me. I have not spent a large portion of my life and income on improving myself to take it to the grave without sharing!

Pfizer COVID Vaccine Deadly

Pfizer COVID Vaccine Deadly

Pfizer doesn’t want you to know this. This information doesn’t appear in any of their ads for the COVID vaccine for some reason. Baffling for sure!
Executive summary

The easiest way to tell if you are talking to someone who is intellectually honest about the COVID vaccines is to ask them for their assessment of the Levi paper.

If they claim, like UPenn Professor Jeffrey Morris does, that there is nothing to see here, then you are dealing with someone who is intellectual dishonest. The AI analysis of Morris’s attack on the Levi paper is absolutely devastating.
What the paper found

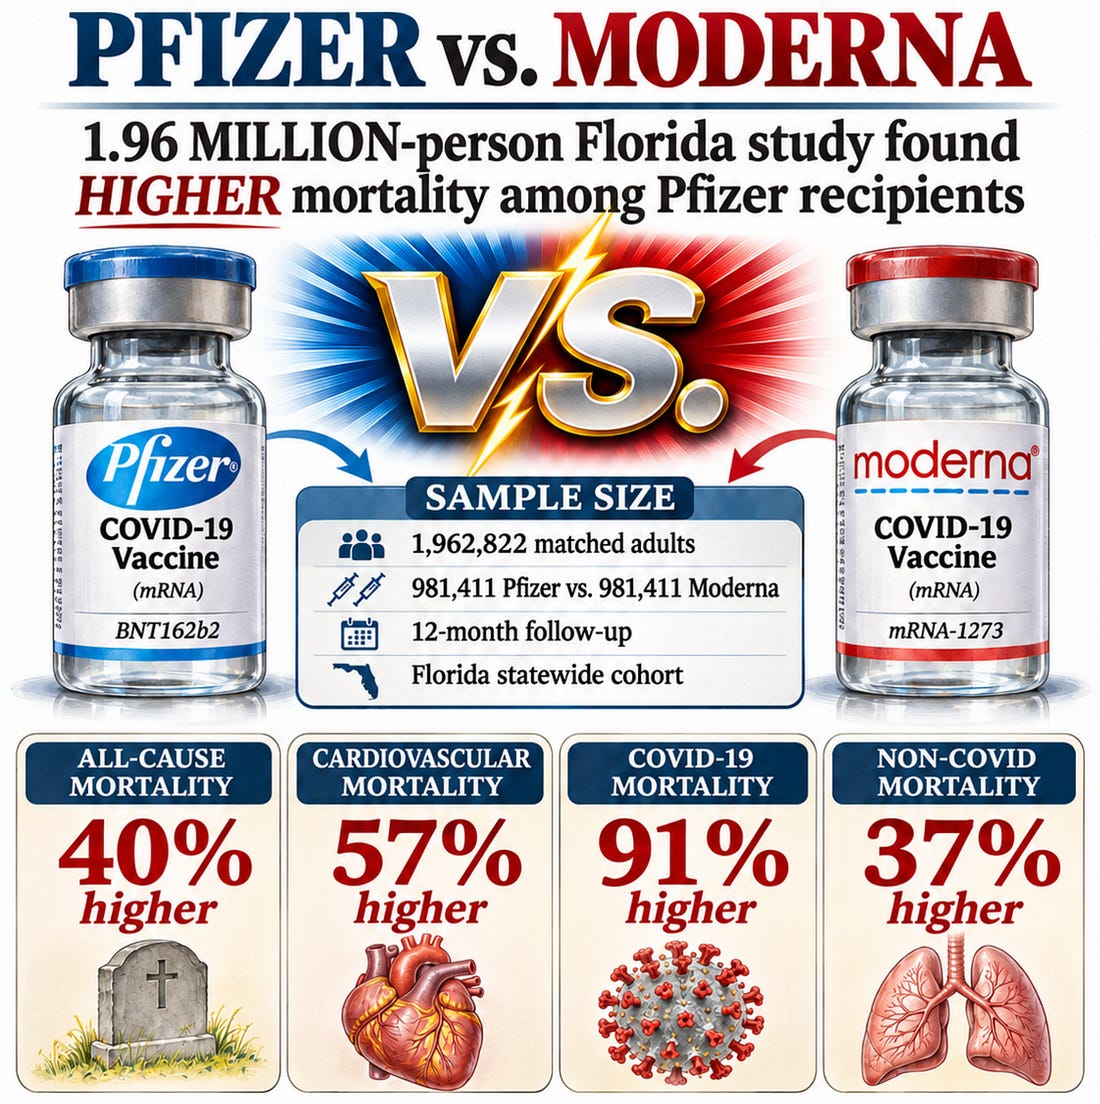
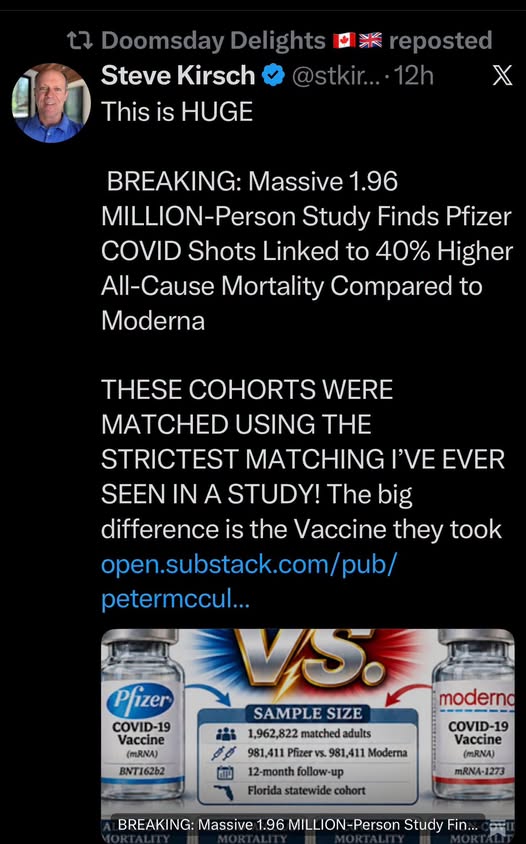
37% higher non-COVID mortality in people who got Pfizer.

That’s a train wreck.

There is no other way to spin this.

Possible explanations for the results:

The Pfizer/Moderna groups weren’t really matched

Moderna reduces non-COVID all-cause mortality by 37%

The problems:

They were matched. Barbra Dickerman wrote 2 papers on COVID vaccines and VA data showing that crude demographic matching creates extremely good morbidity matching to nobody’s surprise. But Levi’s matching was MUCH stronger than what Dickerman did (more attributes and tighter matches). And he confirmed the matching by looking at the single most devastating statistic: prior cardiovascular hospitalization rates were matched. This is not a random marker — it’s arguably the single most mortality-relevant clinical signal you can extract from administrative data. So we have no reason to believe the groups weren’t matched and every reason to believe they were.

There is no mechanism of action that could possibly explain how a COVID vaccine can reduce non-COVID all-cause mortality by 37%. If that were true, this would be the most amazing drug ever created. Moderna would be marketing their COVID vaccine as a fountain of youth. Everyone would be taking it. We’d have seen dramatic reduction in all cause mortality all over the world after rolling out the drug. No such data exists. If you plot cumulative COVID deaths over time for the world, the rollout of the vaccine didn’t change the slope one bit which means the COVID shots didn’t really save any lives. But people who opt to taking vaccines have lower mortality in general, but it is NOT caused by vaccines; it is 100% selection bias. People who opt for vaccines tend to have better access to healthcare.

The full discussion is here and it’s worth reading.
The bottom line

No two ways about it. The COVID vaccines were deadly.

They should be taken off the market.

It is absolutely appalling that businesses and schools forced people to take a vaccine that can increase mortality by 37%. But nobody is willing to talk about it, and no business has formally apologized for their mistake.

Those who want to talk about, like Professor Morris, cherry pick the evidence to support their point of view. These people are extremely dangerous. The AI analysis of Morris’s attack on the Levi paper is absolutely devastating.
Where is the outrage?

Every member of Congress should be shocked by this paper. They should be calling for replication of this study in all 50 states.

Don’t they want to know that they were responsible for over 500,000 American deaths?

Can you name one member of Congress doing that? With 535 members, you’d think that there would be at least one honest member speaking out asking for similar studies to be done, wouldn’t you?

Not one.

They don’t want to know.

Summary

The Levi paper is clear: 37% higher mortality if you got Pfizer.

None of the “explanations” can explain this difference.

Nobody is calling for more studies to replicate the Levi study.

And the Levi study was rejected by around 12 journals before being published showing you just how corrupt “science” is.

https://open.substack.com/pub/stevekirsch/p/levi-paper-showing-pfizer-is-a-toxic

Notes on my Brownstone Annual Conference Speech

Dr Robert Malone Speech Notes

(Tom: A great article giving a perspective on the last 6 years and why no accountability is developing.)

TWO QUOTES TO SET THE FRAME

The two quotes:

The first, from Robert Hunter, the bard of the Grateful Dead. And this quote may reflect something of my misspent youth: What a long, strange trip it’s been.

The second, widely attributed and of uncertain origin. We certainly live in interesting times.

https://open.substack.com/pub/rwmalonemd/p/notes-on-my-brownstone-annual-conference

NZ Whistle Blower Barry Young

NZ Whistle Blower Barry Young

BREAKING: New Zealand whistleblower Barry Young: “They RAIDED my home and ARRESTED me for exposing deadly COVID vaccine batches.”

Catastrophic death rate PFIZER batches:
Batch 1: 152 deaths out of 711 vaccinated 21.4% dead.
Batch 2: 38 deaths out of 221 17.2% dead.
Batch 3: 48 deaths out of 310 15.5% dead.

Normal background death rate in that period? Only 0.75%.

The statistical odds of this happening by chance? Roughly 1 in 100 BILLION.

His direct conclusion: “Statistically, there is no way this vaccine ISN’T killing people.”

Yet instead of launching an investigation… authorities raided his home and arrested him.